Patient Credit Balances Are a Compliance Clock: Refund Workflows, the Medicare 60-Day Rule, and Escheatment
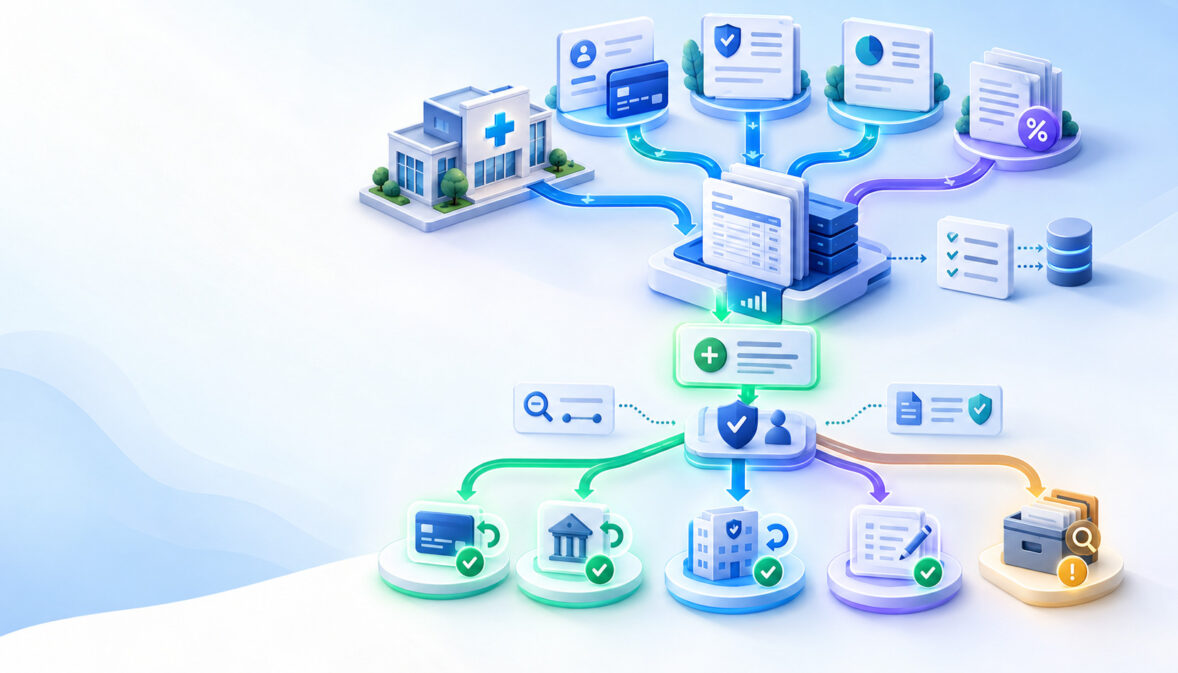
A sound patient credit balance refund workflow identifies every credit, reconciles the account, determines whether the money belongs to the patient, Medicare, another payer, or another account, returns it through the appropriate process, documents what happened, and tracks unresolved patient-owned funds under applicable state unclaimed-property law. Medicare’s 60-day rule does not apply automatically to patient credits.
A negative balance in a medical billing system is not itself proof that a refund is due. It can represent a true patient overpayment, a payer overpayment, duplicate payment, posting error, unapplied patient credit, contractual adjustment problem, failed refund, or money posted to the wrong patient or encounter.
That distinction is the foundation of revenue cycle credit balance management. A medical practice should treat every credit as an open financial obligation that requires classification and disposition—not as a harmless negative accounts-receivable number that can remain on the ledger indefinitely.
| Credit Type | Likely Owner | Primary Rule Set | Immediate Action |
| Patient overpayment | Patient or guarantor | State law, contracts and practice policy | Reconcile and issue refund when ownership is confirmed |
| Medicare overpayment | Medicare | Social Security Act §1128J(d); 42 CFR §401.305 | Investigate, quantify as applicable, report and return correctly |
| Commercial-payer overpayment | Commercial payer | Payer contract and applicable law | Follow payer-specific recovery or return procedure |
| Duplicate payment | Depends on payment source | Contract, payment and accounting rules | Verify which payment should remain |
| Misapplied payment | Depends | Accounting and billing rules | Correct posting before issuing funds |
| Unclaimed patient refund | Patient until properly reported/remitted | Controlling state unclaimed-property law | Conduct due diligence and track escheatment requirements |
The practical rule is straightforward: determine ownership before determining the refund process.
What Does a Patient Credit Balance Actually Mean?
A patient account credit balance exists when credits posted to an account exceed the charges or patient responsibility currently allocated to that account. It is an accounting condition, not necessarily a refund decision.
A true patient overpayment means reconciliation has established that the patient or guarantor paid more than the amount properly due. An unapplied patient credit, by contrast, may simply be money that has not yet been assigned to the correct encounter, invoice, guarantor, provider, or charge.
A payer overpayment is another category entirely. If Medicare paid a practice money to which the practice is not entitled after applicable reconciliation, federal Medicare overpayment requirements can apply. A commercial-payer credit normally requires review of the applicable payer contract, adjustment history, and refund or recoupment procedure.
A posting error can create the appearance of a refund without any excess cash actually being held. That is why a patient credit balance refund workflow must begin with reconciliation rather than a refund button.
Duplicate postings, incorrect adjustments, and incomplete account updates can create apparent credit balances before a refund is actually owed. Building controls that reduce medical billing and payment-posting errors helps the billing team correct those problems before an account enters the patient refund queue.
How Medical Billing Credit Balances Are Created
Medical billing credit balances frequently begin before final claim adjudication.
A practice may collect an estimated deductible or coinsurance amount at check-in. Once the claim is adjudicated, the payer may assign less responsibility to the patient than originally estimated.
Other common causes include:
- an estimated copay, coinsurance amount, or deductible collected before adjudication;
- patient payment exceeding final patient responsibility;
- duplicate card payments;
- duplicate ACH, check, lockbox, or portal payments;
- a payer payment posted after the patient has already paid;
- secondary coverage paying after patient collection;
- a coordination-of-benefits correction;
- a contractual adjustment entered after collection;
- corrected or reversed claims;
- payer takebacks that change how prior payments should be allocated;
- money posted to the wrong patient, guarantor, date of service, provider, or location;
- an unapplied patient credit waiting for allocation; and
- card, ACH, or check refunds that were recorded in the practice-management system but failed operationally.
Consider an illustrative example. A practice collects $180 before an office procedure based on an eligibility estimate. The final EOB assigns $95 to the patient. After the billing team confirms that primary and secondary adjudication is complete, contractual adjustments are correct, and no legitimate offset changes the account, the remaining $85 is a patient-owned credit.
That $85 is now part of the patient refund workflow. The negative balance alone did not establish that result; reconciliation did.
The First Rule of a Patient Credit Balance Refund Workflow: Determine Who Owns the Money

The fastest way to create refund errors is to assume every negative balance belongs to the patient.
A reliable patient credit balance refund workflow should follow this sequence:
- Reconcile the account ledger: Review charges, payments, adjustments, reversals, refunds, write-offs, transfers, and voids.
- Verify adjudication: Confirm whether the primary payer has completed processing and whether known secondary coverage remains pending.
- Identify the original payment source: Patient card, ACH, check, Medicare, commercial payer, employer, guarantor, or another source.
- Confirm contractual adjustments: Make sure the allowed amount and contractual write-off were posted accurately.
- Check later activity: Look for corrected claims, payer recoupments, secondary payments, charge reversals, or earlier refunds.
- Determine the owner of the credit.
- Assign the correct workflow: Patient refund, Medicare return, commercial-payer return, posting correction, authorized transfer, or unclaimed-property tracking.
This process should be visible in the patient credit balance report rather than depending on individual staff memory.
Credit research often depends on information collected before the claim reaches the billing team. Better coordination between the front desk and medical billing staff helps preserve insurance details, payment-source information, authorization status, patient communications, and other facts needed to determine why a credit exists and who owns it.
Medicare’s 60-Day Overpayment Rule: Where It Applies—and Where It Does Not
The Medicare 60-day overpayment rule is one of the most frequently misunderstood parts of credit-balance management.
Section 1128J(d) of the Social Security Act requires a person who has received an overpayment to report and return it by the later of:
- 60 days after the overpayment is identified; or
- the date a corresponding cost report is due, if applicable.
The statute defines an overpayment as funds received or retained under Medicare or Medicaid to which the person, after applicable reconciliation, is not entitled.
Under Social Security Act §1128J(d), a Medicare or Medicaid overpayment generally must be reported and returned by the later of 60 days after the overpayment is identified or the date an applicable corresponding cost report is due.
For ordinary physician practices and suppliers dealing with Medicare Parts A and B overpayments, 42 CFR Part 401 provides the implementing regulation. The regulation expressly covers providers and suppliers under Medicare Parts A and B.
| Question | Medicare Overpayment | Patient Overpayment |
| Who owns the funds? | Medicare/federal program | Patient or guarantor |
| Main authority | Federal statute and Medicare regulation | Applicable state law, contracts and practice policy |
| Does the federal 60-day rule potentially apply? | Yes, when the federal requirements are satisfied | Not merely because a patient has a credit |
| Correct resolution | Report and return through applicable Medicare procedure | Refund or otherwise lawfully dispose of patient-owned funds |
A patient who overpaid a deductible estimate is not transformed into a Medicare overpayment simply because Medicare adjudicated the underlying claim.
Likewise, the existence of a Medicare beneficiary on an account does not make every credit subject to the Medicare 60-day overpayment rule. Ownership and source of funds still control the analysis.
What Does “Identified” Mean Under the Current Medicare Rule?
This point changed and deserves special attention.
The current version of 42 CFR §401.305(a)(2) states that a person identifies an overpayment when the person knowingly receives or retains an overpayment. “Knowingly” uses the definition in the False Claims Act at 31 U.S.C. §3729(b)(1)(A).
That is different from the older regulatory formulation frequently described in pre-2025 compliance material as a “reasonable diligence” standard.
CMS amended §401.305 in its CY 2025 Physician Fee Schedule final rule. The change became effective January 1, 2025. The current regulation therefore should control a September 2026 healthcare overpayment refund analysis rather than older summaries of the 2016 rule.
For Medicare Parts A and B providers and suppliers, the current 42 CFR §401.305 overpayment regulation states that an overpayment is identified when a person knowingly receives or retains it and also establishes the reporting-and-return framework, conditional investigation suspension, and applicable lookback rule.
Identification Does Not Necessarily Wait for Exact Quantification
CMS addressed this issue directly in the 2024 final rule.
CMS explained that the 60-day period begins when an overpayment is identified under §401.305(a)(2), even when the precise amount has not yet been calculated.
However, the amended regulation contains an important investigation provision.
If:
- a person has identified an initial overpayment;
- the person has not finished a good-faith investigation into related overpayments arising from the same or a similar cause; and
- the person conducts that investigation timely and in good faith,
the deadline for reporting and returning the initial and related overpayments is suspended.
Under §401.305(b)(3), that suspension ends at the earlier of:
- the date the investigation concludes and the aggregate amount is calculated; or
- 180 days after the initial identified overpayment was identified.
This does not mean every practice receives an automatic additional 180 days.
CMS’s final-rule explanation makes that clear: if a qualifying investigation does not occur, the ordinary deadline is not suspended. If the suspension ends before the full 60-day period has run, the provider has the remainder of that original 60-day period.
The Six-Year Lookback
For overpayments subject to 42 CFR §401.305, the regulation requires reporting and return when the overpayment is identified within six years of the date the overpayment was received.
That six-year Medicare lookback should not be confused with:
- a patient’s state-law refund rights;
- state unclaimed-property dormancy;
- an internal credit balance aging report; or
- a processor’s software history window.
They are different concepts operating under different rule sets.
How Does a Practice Report and Return a Medicare Overpayment?
Section 401.305 directs providers to use an applicable claims adjustment, credit balance, self-reported refund, or another reporting process established by the applicable Medicare contractor.
CMS’s current Medicare Financial Management Manual also provides operational guidance for Medicare contractors processing unsolicited or voluntary refunds, including the claim-specific information needed to apply the repayment correctly.
Once a Medicare overpayment must be returned, the practice should use the applicable claims-adjustment, credit-balance, self-reported-refund, or contractor process and retain enough information to connect the repayment to the affected claim.
The CMS Medicare Financial Management Manual explains the financial-management procedures Medicare contractors use when processing overpayments and voluntary refunds.
That creates an important control: a Medicare overpayment should not simply be mailed back as though it were an ordinary patient overpayment refund.
Patient Refunds Should Follow the Original Payment Method When the Card Rules Require It

Card refunds create a second area where practices can easily confuse network rules with software limitations.
When the original payment was made with Visa, the practice should start with the transaction-linked card refund process rather than automatically substituting cash or a check. Under the current Visa rules for refunds to the original payment credential, a merchant must, to the extent possible, process a refund for a previous purchase to the same payment credential while following the specified alternative procedures when that cannot be done.
Mastercard’s publicly posted Transaction Processing Rules similarly state that a price adjustment involving a Mastercard purchase generally must be credited to the same card account used for the purchase, or a card reissued by the same issuer to the same cardholder. The rules also recognize situations involving an unavailable original card or a declined refund authorization.
Those rules explain why the patient refund original payment method principle should be built into the practice’s refund procedures rather than left to staff preference.
Why Cash Is Usually the Wrong Default for a Card-Funded Credit
Turning a card-funded transaction into cash without first following the supported refund procedure can weaken reconciliation and fraud controls.
It separates the original payment from the refund, creates additional handling risk, and can make it harder to prove that the appropriate cardholder actually received the money.
A good medical practice refund policy should therefore tell staff:
- start with the original transaction and processor-supported refund procedure;
- process a partial refund where only part of the original payment is being returned;
- use stored tokens rather than manually handling full card data where the platform supports tokenized refunds;
- do not invent or manually substitute a new card number;
- escalate failed, unavailable, or old transactions to the processor/acquirer;
- document any authorized alternative refund method.
When a refund originates from a payment portal or stored-card transaction, staff should use the existing token and transaction reference rather than copying full card details into billing notes or spreadsheets.
Appropriate healthcare payment security and tokenization controls can preserve the connection to the original payment while reducing unnecessary exposure of payment information.
Expired, Replaced, and Closed Cards
An expired plastic card does not necessarily mean the underlying account relationship has disappeared. The practice should therefore attempt or investigate the transaction-linked refund process rather than automatically issuing a check.
When the account is closed or the original refund is declined, follow the applicable network and processor/acquirer procedure.
Visa expressly provides circumstances where a secondary payment credential or alternate refund can be used. Mastercard also recognizes exceptions where the original card is unavailable or a refund authorization is declined.
There Is No Universal Gateway Refund Window
A processor may allow staff to click “refund” for only a certain period after a transaction. Another platform may offer different functionality.
That software limitation is not automatically a Visa or Mastercard rule.
If an old payment can no longer be refunded through the normal portal, the patient refund workflow should require staff to contact the processor or acquiring bank for the appropriate procedure rather than inventing a deadline or improvising a new card transaction.
The Monthly Patient Credit Balance Refund Workflow
The best way to keep credits from becoming stale is to make the patient credit balance refund workflow a recurring revenue-cycle control.
Step 1: Run the Patient Credit Balance Report
A useful patient credit balance report should contain at least:
- patient or guarantor identifier;
- account number;
- encounter/date of service;
- provider and location;
- payer;
- original payment source;
- payment method;
- original transaction date;
- credit amount;
- reason code;
- age of credit;
- last account activity;
- current refund eligibility;
- assigned owner;
- research status;
- refund or escheatment deadline field;
- disposition date; and
- link or reference to supporting documentation.
The report should include every relevant credit, not merely balances above an arbitrary dollar threshold.
Step 2: Correct Posting Errors
Remove duplicate postings, incorrect allocations, reversed charges, incorrectly entered adjustments, and obvious unapplied cash from the refund queue.
An unapplied patient credit should first be investigated to determine where the money belongs.
Step 3: Verify Payer Adjudication
Review the current EOB or ERA, contractual adjustment, corrected claims, secondary coverage, coordination-of-benefits information, and payer recoupments.
Do not issue patient overpayment refunds merely because a negative balance appeared before final payer activity was posted.
Step 4: Identify Ownership
Classify each item as:
- patient or guarantor money;
- Medicare money;
- commercial-payer money;
- misapplied cash;
- unresolved credit; or
- another documented category.
Ownership should be an explicit field in the patient credit balance report.
Step 5: Segregate Medicare Overpayments
Potential Medicare overpayments should leave the routine patient queue and enter the practice’s Medicare compliance process.
That separation is one of the strongest controls in a credit balance audit medical practice workflow because it stops staff from treating a federal-program overpayment as a patient refund.
Step 6: Validate Patient-Owned Credits
Confirm the final amount payable to the patient, previous refund activity, current contact information, original payment method, and any authorized application of the money.
Do not assume that an old patient account credit balance may simply remain on the account because the patient could return.
Step 7: Determine the Refund Channel
Match card money to the supported card refund process, ACH money to the appropriate ACH/accounting process, and check or cash payments to the practice’s controlled disbursement procedure.
The patient refund original payment method control should be documented rather than based on whichever method is easiest for staff.
Step 8: Obtain Approval
Separate research, approval, and payment-release duties for material refunds where practical.
The practice can create internal approval levels, but it should not describe those levels as legal thresholds unless a controlling rule actually creates one.
Step 9: Issue the Refund or Return
Capture:
- date;
- amount;
- payment method;
- processor or bank reference;
- check number where applicable;
- approving employee;
- patient notification; and
- related ledger entry.
Step 10: Reconcile the Refund
A refund is not complete simply because the patient ledger says “refunded.”
Reconcile the practice-management system to:
- processor settlement activity;
- bank activity;
- general ledger;
- patient account; and
- refund exception report.
This is an important part of revenue cycle credit balance management, especially where multiple systems can record a transaction independently.
Step 11: Escalate Failed or Undeliverable Refunds
Track:
- returned checks;
- stale checks;
- rejected ACH credits;
- declined card refunds;
- closed accounts;
- invalid addresses; and
- unsuccessful patient outreach.
Those balances can eventually become unclaimed patient refunds rather than disappearing from the practice’s books.
Step 12: Track State Unclaimed-Property Requirements
Once the practice cannot return confirmed patient-owned money, the patient credit balance refund workflow must transition from ordinary refund operations into an unclaimed-property process.
Build a Credit Balance Aging Report Before Credits Become Old
A credit balance aging report helps management distinguish recently created credits from unresolved balances that need escalation.
| Aging | Management Priority | Typical Operational Action |
| 0–30 days | Reconciliation | Verify postings and final adjudication where appropriate |
| 31–60 days | Investigation | Establish payment source and ownership |
| 61–90 days | Escalation | Complete confirmed patient and payer dispositions |
| 91–180 days | High priority | Management review of unresolved exceptions |
| 181–365 days | Compliance review | Intensify refund attempts and state-law review |
| More than one year | Exception management | Review unclaimed-property exposure and unresolved liabilities |
These are management intervals, not universal legal deadlines.
A 31-day-old Medicare overpayment can raise a different issue from a 181-day-old ordinary patient refund. Likewise, a processor’s refund-interface limitation does not change a state’s escheatment rule.
The credit balance aging report should therefore contain separate fields for operational age and actual legal or contractual deadlines.
When Do Unclaimed Patient Refunds Become Unclaimed Property?
A confirmed patient refund does not become practice income simply because the patient cannot be found.
The typical lifecycle is:
credit identified → ownership confirmed → refund due → owner outreach → failed or uncashed refund → dormancy tracking → statutory due diligence → report and remittance when required
This is where unclaimed property escheatment patient refunds become a distinct compliance issue.
State law determines the relevant property classification, dormancy period, due-diligence requirement, reporting cycle, remittance method, and record-retention obligation.
There is no single national three-year or five-year rule for every medical practice.
Which State Gets the Property?
For intangible unclaimed property, interstate priority rules matter.
The U.S. Supreme Court’s Texas v. New Jersey framework provides that property ordinarily goes first to the state of the owner’s last-known address shown in the holder’s records, provided that state has authority to take the property. Where no owner address is shown, the secondary rule generally looks to the holder’s state of incorporation.
That means a multi-state practice should preserve a patient’s last-known address as part of its unclaimed patient refunds record.
It should not automatically remit every old credit to the state where the physician’s office happens to be located.
State Escheatment Rules Are Not Uniform
Verified September 30, 2026. The examples below illustrate why a practice should not build one national rule into its medical practice refund policy.
| State | Official Guidance Relevant to Patient/Customer Credits | Dormancy / Due Diligence | Reporting Timing |
| California | SCO’s codes list customer overpayments (MS05), A/R credit balances (MS09), and refunds due (MS11) | These listed categories use a 3-year dormancy period. Due diligence generally applies to reportable property of $50 or more and occurs before reporting. | Most holders file a Notice Report before Nov. 1 and a Remit Report June 1–15. |
| New York | OSC lists consumer credit balances/credit checks or memos under its consumer-credit framework | Current table lists 3 years. OSC requires owner due diligence before transfer, with timing depending on the applicable reporting schedule and value. | Consumer credit balance schedule currently uses a Dec. 31 cut-off and Feb. 15 final report/remittance date. |
| Pennsylvania | Treasury codes include customer overpayments, A/R credit balances and refunds due among reportable property types | Most such non-exception property uses 3 years. Required notice generally must be sent 60–120 days before reporting when statutory conditions are met. | Annual report is generally due April 15. |
| Florida | DFS includes credit balances, overpayments and refunds within unclaimed-property administration | Florida commonly uses a 5-year period for this class of general property, but the exact classification must be checked. Due diligence generally applies to property of $50 or more and is conducted 60–120 days before filing. | Report and remittance are due before May 1 for the preceding calendar year’s reportable property. |
| Texas | Comptroller guidance recognizes overpayments as unclaimed property and requires holders to determine the abandonment period by property type | The applicable period must be confirmed against the current Texas property-type table rather than inferred from another state’s rule. | March 1 is the annual cut-off; owner notice is due no later than 60 days before the July 1 reporting/remittance deadline. |
California’s official unclaimed-property dormancy schedule assigns three-year dormancy periods to categories including customer overpayments, accounts-receivable credit balances, and refunds due. A medical practice still needs to determine which property classification actually fits the patient credit before calculating its reporting timeline.
New York’s current Office of the State Comptroller materials list consumer credit balances/credit checks or memos at three years and show the applicable consumer-credit reporting schedule.
Pennsylvania Treasury’s holder instructions state that most property types use three years and that the 2025 property report was due April 15, 2026; its due-diligence guidance requires qualifying owner notice between 60 and 120 days before reporting.
Florida’s current DFS reporting manual requires qualifying due diligence not more than 120 and not less than 60 days before filing and requires reports before May 1.
Texas’s official Comptroller instructions emphasize that abandonment periods vary by property type and require owner notices no later than 60 days before the July 1 report/remittance deadline. Texas also requires holders to retain records of reports for at least 10 years.
The takeaway is not “use three years.” The takeaway is classify the property and verify the controlling state’s current rule.
That is the safest way to handle unclaimed property escheatment patient refunds.
Do Not Write Old Patient Credits Off to Income
An old liability does not become practice revenue simply because staff stopped working it.
If money still belongs to a patient, state unclaimed-property law may require the practice to preserve that liability, perform due diligence, and eventually report and remit it.
An accounting write-off cannot replace the legal analysis.
Likewise, a small dollar amount should not automatically be erased. Some states create specific thresholds or exceptions for certain property, while others still require reporting or aggregation.
A medical practice refund policy can contain internal materiality and approval rules, but staff should not confuse them with ownership law.
How Better Pre-Service Estimates Reduce Patient Overpayment Refunds
The cleanest patient refund workflow is the one that avoids unnecessary overcollection in the first place.
Before collecting an estimated amount, practices should use available information concerning:
- eligibility;
- known copays;
- deductible status;
- coinsurance;
- contracted rates;
- benefit information;
- prior authorization status;
- known secondary insurance; and
- prior payments or deposits.
The estimate should be communicated as an estimate—not as final adjudicated responsibility.
Where final responsibility is uncertain, an appropriate partial deposit may create less refund work than automatically collecting the highest plausible amount.
Then build reconciliation into the post-adjudication process:
eligibility → estimate → patient collection → claim → EOB/ERA → reconciliation → refund if owed
That final reconciliation step is critical to reducing both patient overpayment refunds and old medical billing credit balances.
Improved estimates do not justify holding a confirmed refund merely because the patient may receive future services.
Documentation That Makes a Credit Balance Audit Defensible
Every disposition should leave an audit trail.
| Disposition | Documentation to Retain |
| Patient refund | Original transaction, ledger, reason for credit, EOB/ERA if relevant, approval, refund method, processor/check reference, date, patient notice, failed attempts |
| Applied to another balance | Legal/contractual basis, patient or guarantor relationship, authorization where appropriate, destination account, posting history, approval |
| Medicare/commercial-payer return | Payer, claim, overpayment reason, amount, reporting method, correspondence, confirmation/reference, adjustment trail |
| Escheated | Owner data, date payable, property classification, dormancy calculation, due-diligence evidence, returned mail, state report, remittance evidence, report year, accounting entries |
A credit balance audit medical practice process should also be able to reconstruct who researched the credit, who approved the disposition, who released the funds, and who reconciled the transaction.
Do not transfer patient money casually among unrelated accounts or family members. The practice should establish a valid contractual, legal, or authorized basis before applying one person’s funds to another obligation.
This documentation is what converts revenue cycle credit balance management from a housekeeping exercise into a defensible financial-control process.
Internal Controls for Patient Refunds
A patient credit balance refund workflow is strongest when no single employee controls every step.
Depending on practice size, consider separating:
- credit research;
- ownership determination;
- refund approval;
- payment release; and
- reconciliation.
Use standardized refund reason codes rather than unrestricted free text.
Generate exception reports for:
- refunds exceeding the original payment;
- duplicate refunds;
- manual checks replacing card refunds;
- refunds to an account different from the original funding source;
- deleted or modified credit entries;
- failed refunds;
- reopened credits;
- refunds followed by payer recoupments; and
- credits remaining unresolved beyond internal aging targets.
Restrict administrator rights that allow staff to modify transaction history or refund destinations.
The patient credit balance report and processor refund report should reconcile to the bank and general ledger.
A Practical Monthly Credit-Balance Review Calendar
This schedule is operational guidance, not a statutory timetable.
Week 1 — Generate and Classify
Run the credit balance aging report and classify new credits by payment source, owner, payer, age, and reason.
Correct obvious posting errors immediately.
Week 2 — Investigate
Review EOBs, ERAs, contractual adjustments, secondary insurance, duplicate transactions, recoupments, corrected claims, and unapplied cash.
Escalate government-program issues separately.
Week 3 — Refund and Return
Complete validated patient overpayment refunds, Medicare returns, commercial-payer returns, and authorized posting corrections.
Reconcile each transaction.
Week 4 — Escalate Unresolved Credits
Review failed refunds, old patient account credit balance items, unresolved ownership questions, returned mail, and approaching state unclaimed-property milestones.
Update the patient credit balance refund workflow dashboard so every item has a responsible owner and next action.
Common Credit-Balance Mistakes
The most common mistakes are not complicated. They usually come from using one rule for several different categories of money.
Avoid:
- assuming every negative balance belongs to the patient;
- applying the Medicare 60-day overpayment rule to ordinary patient-owned credits;
- assuming the federal 60-day clock starts only after exact quantification;
- treating the current investigation provision as an automatic 180-day extension;
- leaving confirmed refunds open indefinitely because the patient might return;
- refunding card-funded payments in cash without reviewing network and processor procedures;
- treating a gateway’s software limitation as a Visa or Mastercard rule;
- repeatedly mailing checks without documenting returned mail;
- moving patient credits across unrelated accounts without authority;
- writing old credits into miscellaneous income;
- using one state’s dormancy period nationwide;
- ignoring the patient’s last-known address in interstate unclaimed-property analysis;
- failing to reconcile processor refunds to the billing ledger; and
- issuing a duplicate refund after later payer activity changes the account.
Practical Example 1: Estimated Patient Responsibility
Illustrative amounts: A practice collects $300 before a procedure based on a benefits estimate.
After adjudication, the EOB assigns $190 to the patient. Billing confirms the contractual adjustment, verifies that no secondary claim is pending, and finds no other authorized balance to which the money may lawfully be applied.
The resulting $110 becomes a confirmed patient credit.
The practice:
- validates the original payment;
- classifies the $110 as patient-owned;
- routes the transaction through the supported card-refund process;
- records the approval and processor reference;
- posts the refund to the patient ledger;
- reconciles it to processor settlement and bank activity.
The patient credit balance refund workflow is complete only after the accounting systems agree.
Practical Example 2: Unreachable Former Patient
A former patient has a confirmed $75 credit. The amount and timeline are illustrative.
The practice verifies the last-known address and issues an authorized refund. The check is returned as undeliverable.
The practice does not write the $75 into income.
Instead it:
- records the failed refund;
- preserves the patient’s last-known address;
- maintains the balance as an unresolved liability;
- determines which state’s unclaimed-property law controls;
- identifies the appropriate property classification;
- tracks the correct dormancy period;
- performs required statutory due diligence;
- reports and remits the property if it remains unclaimed.
That is the lifecycle for unclaimed patient refunds.
Frequently Asked Questions
Do all patient credit balances have to be refunded within 60 days?
No. There is no universal federal rule requiring every patient credit to be refunded within 60 days.
The federal Medicare 60-day overpayment rule concerns qualifying Medicare and Medicaid overpayments under Section 1128J(d). Ordinary patient-owned credits may instead implicate state law, patient agreements, payer arrangements, and eventually state unclaimed-property requirements.
Does the Medicare 60-day rule apply to patient overpayments?
Not simply because Medicare processed the underlying claim.
First determine who owns the money. If the excess funds belong to the patient or guarantor, the ordinary patient refund and applicable state-law process applies. If the money is a Medicare overpayment covered by 42 CFR §401.305, the federal reporting-and-return rules apply.
When does Medicare consider an overpayment identified?
Under the current Parts A/B regulation, a person identifies an overpayment when the person knowingly receives or retains it, with “knowingly” using the False Claims Act definition.
CMS changed the regulatory language effective January 1, 2025, so older descriptions based solely on the former reasonable-diligence formulation should not be used as the current rule.
Can a medical practice apply a patient credit to a future visit instead of refunding it?
Possibly in appropriate circumstances, but do not assume a practice may hold a confirmed patient refund indefinitely. The practice should review applicable state law, payer arrangements, patient agreements, account relationships, and authorization requirements. Any application of funds should be documented clearly.
Can I refund an old credit-card payment by check?
Sometimes, but a check should not automatically replace the card-refund process.
Visa and Mastercard rules address refunds back to the original payment credential/account and provide circumstances for alternate treatment. If the processor no longer exposes the original transaction in its software, obtain processor/acquirer instructions before improvising.
What happens if a patient refund check is never cashed?
The underlying liability may remain outstanding.
The practice should track the uncashed check, verify whether the patient can be contacted, and determine whether the property eventually becomes reportable under the controlling state’s unclaimed-property law.
How long can a medical practice hold an unclaimed patient credit?
There is no universal national dormancy period.
The answer depends on the controlling state, property type, dormancy trigger, owner contact, and other state-specific requirements. California, New York and Pennsylvania commonly use three years for relevant categories discussed above, while Florida commonly uses a longer general period. Classification must still be verified rather than assumed.
Can small patient credits simply be written off?
Do not adopt a universal de minimis write-off rule.
Some states have particular thresholds or exclusions, but those rules vary. Internal materiality policies can control workflow and approval, but they do not automatically eliminate a patient’s ownership rights.
How often should a medical practice run a credit-balance report?
Monthly is a strong operational cadence for most small and midsize practices because it keeps medical billing credit balances visible and assigned.
It is a management recommendation rather than a universal legal requirement. Medicare overpayments, payer contracts, state refund requirements, and escheatment rules may create separate deadlines.
Make the Patient Credit Balance Refund Workflow a Monthly Control
The operating sequence should remain:
identify → reconcile → determine ownership → refund or return → document → monitor unresolved property
A mature patient credit balance refund workflow does not put every credit on one clock. Medicare overpayments, commercial-payer overpayments, patient money, posting errors, unapplied cash, and unclaimed property may all appear on the same report while following different legal and operational rules.
That is why effective revenue cycle credit balance management combines a monthly patient credit balance report, disciplined ownership determination, a defensible medical practice refund policy, controlled refund processing, reconciliation, a credit balance aging report, and state-specific escheatment tracking.
The management objective is not simply to make negative numbers disappear.
It is to make sure every credit has a documented owner, a documented reason, an accountable employee, an appropriate disposition, and evidence that the money ultimately reached the person or entity legally entitled to it.